PUBLISHER: Mordor Intelligence | PRODUCT CODE: 2119683

PUBLISHER: Mordor Intelligence | PRODUCT CODE: 2119683
Value-based Healthcare Services - Market Share Analysis, Industry Trends & Statistics, Growth Forecasts (2026 - 2031)
According to Mordor Intelligence, value-based healthcare services market size in 2026 is estimated at USD 2.27 trillion, growing from 2025 value of USD 1.93 trillion with 2031 projections showing USD 5.17 trillion, growing at 17.86% CAGR over 2026-2031.
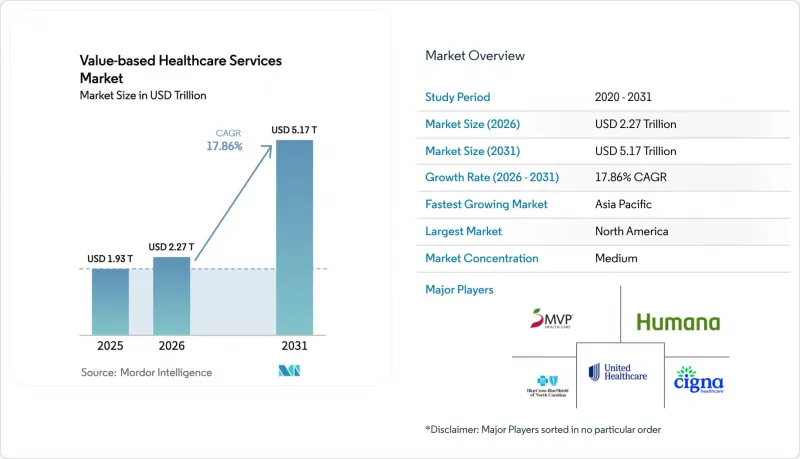
This report is Segmented by Payment Model (Bundled Payments, Shared Savings, Pay-For-Performance, and More), Provider Setting (Hospitals & IDNs, Physician Group Practices, Home Health & Post-Acute Care, Ambulatory Surgical Centres, and More), and Geography (North America, Europe, Asia-Pacific, Middle East & Africa, South America). The Market Forecasts are Provided in Terms of Value (USD).
Global Value-based Healthcare Services Market Trends and Insights
Rising Burden of Chronic Diseases & Aging Population
Adults aged 65 and older will number 73 million in the United States by 2030, with 85% living with at least one chronic ailment and 60% managing multiple conditions. This cohort already drives over half of hospital admissions and pushes healthcare costs upward. The value-based healthcare services market incentivizes coordinated management through shared savings arrangements that encourage preventive interventions and reduce avoidable hospitalizations. Providers leverage longitudinal data, home-based monitoring, and multidisciplinary care teams to address complex needs, generating measurable quality gains and cost offsets.
Government-Led Shift Toward Alternative Payment Models
Policy is a decisive catalyst. The CMS Innovation Center has retired programs that failed to save money while rolling out mandatory episode bundles such as the Transforming Episode Accountability Model, which will involve 741 hospitals from January 2026. Internationally, nations like the Netherlands have adopted bundled payments that improve care protocol adherence without raising total spend. Such mandates hasten provider migration away from fee-for-service toward risk-bearing arrangements.
Dual Revenue-Cycle Complexity (FFS vs VBC)
Running parallel billing systems for fee-for-service and value contracts strains finance departments, particularly in smaller organizations lacking enterprise IT resources. Staff must reconcile divergent coding, documentation, and reporting rules, diverting time and increasing administrative overhead. Until a tipping point of revenue shifts under value models, back-office duplication will remain a drag on operational efficiency.
Other drivers and restraints analyzed in the detailed report include:
- Payer-Provider Push for Integrated, Longitudinal Care
- Expansion of Medicare Advantage & Risk-Based ACO Programs
- Limited Readiness for Downside-Risk Exposure
For complete list of drivers and restraints, kindly check the Table Of Contents.
Segment Analysis
Shared savings programs controlled 30.74% of the value-based healthcare services market in 2025, acting as an accessible on-ramp because they initially shield participants from downside exposure. They serve 11 million beneficiaries within Medicare alone and delivered USD 2.1 billion in savings during 2023. The value-based healthcare services market size for capitation/global budgets is forecast to expand at a 19.02% CAGR through 2031 as payers prefer predictable cost envelopes and providers bolster actuarial and care-management capabilities. Bundled Payments gain traction via the mandatory TEAM model covering surgical episodes, while Pay-for-Performance contracts refine quality metrics to include equity components. Patient-Centered Medical Home frameworks increasingly integrate inside broader ACO structures, and episode-based terms now encompass chronic disease cycles, reflecting rising sophistication in defining outcomes. Niche models such as specialty bundles and employer direct contracting add further optionality, illustrating the continuous evolution of payment design in the value-based healthcare services market.
Growing confidence in capitation accelerates investment in care coordination platforms, remote monitoring, and community-based partnerships. Organizations that master population-health analytics can align provider incentives, adjust panel risk, and capture shared savings while maintaining high consumer satisfaction. Those lacking scale gravitate toward collaborative contracting networks that pool actuarial exposure.
Complete Report Scope:
- By Payment Model
- Bundled Payments
- Shared Savings (ACO)
- Pay-for-Performance
- Patient-Centred Medical Home (PCMH)
- Capitation/Global Budgets
- Episode-based Payments
- Other Emerging Models
- By Provider Setting
- Hospitals & IDNs
- Physician Group Practices
- Home Health & Post-Acute Care
- Ambulatory Surgical Centres
- Virtual/Tele-health Providers
- Other Provider Settings
- By Geography
- North America
- United States
- Canada
- Mexico
- Europe
- Germany
- United Kingdom
- France
- Italy
- Spain
- Rest of Europe
- Asia-Pacific
- China
- Japan
- India
- Australia
- South Korea
- Rest of Asia-Pacific
- Middle East & Africa
- GCC
- South Africa
- Rest of Middle East & Africa
- South America
- Brazil
- Argentina
- Rest of South America
- North America
Geography Analysis
North America retained 45.90% share in 2025 because Medicare, Medicaid, and employer adoption set mature precedents for outcome-oriented clauses. Federal alignment towards accountable care is slated to place every traditional Medicare beneficiary within a risk-sharing relationship by 2030. Canada pilots province-based outcome incentives and Mexico links public-sector payment to quality metrics.
Asia Pacific exhibits the steepest trajectory at 25.20% CAGR through 2031, underpinned by large-scale public reform and rapid digital uptake. China experiments with bundled oncology payments across tier-one cities, Japan adjusts its fee schedule to reward prevention among seniors, and India's Ayushman Bharat Digital Mission provides a backbone for claimless electronic reimbursement. Australia's statewide program demonstrates reductions in hospital length of stay via standardized pathways, signaling regional proof of concept.
Europe maintains steady uptake, led by the Netherlands' diabetes bundles that unite primary and specialty teams on shared budgets. Germany integrates quality thresholds into hospital financing. The United Kingdom tests population-based payments within Integrated Care Systems. Southern European states pilot outcome contracts in selected regions. Middle East and Africa display nascent initiatives, with Gulf Cooperation Council members investing in digital registries and South Africa's National Health Insurance Bill incorporating performance clauses. In South America, Brazil's private insurers adopt capitated oncology products and Argentina trials episode payments in public hospitals.
- UnitedHealth Group (Optum)
- Humana Inc.
- CVS Health (Aetna)
- Elevance Health (Anthem)
- Cigna Healthcare
- Kaiser Permanente
- Blue Cross Blue Shield
- MVP Health Care
- Agilon Health
- Aledade
- Signify Health
- Evolent Health
- Lumeris
- Conifer Health Solutions
- Privia Health
- Oak Street Health
- VillageMD
- ChenMed
- CareMore Health
- Centene Corp.
- Clover Health
- Health Catalyst
- GuideWell (Florida Blue)
Additional Benefits:
- The market estimate (ME) sheet in Excel format
- 3 months of analyst support
TABLE OF CONTENTS
1 Introduction
- 1.1 Study Assumptions & Market Definition
- 1.2 Scope of the Study
2 Research Methodology
3 Executive Summary
4 Market Landscape
- 4.1 Market Overview
- 4.2 Market Drivers
- 4.2.1 Rising Burden of Chronic Diseases & Aging Population
- 4.2.2 Government-Led Shift Toward Alternative Payment Models
- 4.2.3 Payer-Provider Push for Integrated, Longitudinal Care
- 4.2.4 Expansion of Medicare Advantage & Risk-Based ACO Programs
- 4.2.5 AI-Enabled Risk Stratification & Predictive Analytics
- 4.2.6 Employer-Funded Value-Based Contracts for Cost Containment
- 4.3 Market Restraints
- 4.3.1 Dual Revenue-Cycle Complexity (FFS vs VBC)
- 4.3.2 Limited Readiness for Downside-Risk Exposure
- 4.3.3 Interoperability Gaps Across Community-Based Providers
- 4.3.4 Physician Burnout from Quality-Reporting Demands
- 4.4 Porter's Five Forces Analysis
- 4.4.1 Threat of New Entrants
- 4.4.2 Bargaining Power of Buyers
- 4.4.3 Bargaining Power of Suppliers
- 4.4.4 Threat of Substitutes
- 4.4.5 Competitive Rivalry
5 Market Size & Growth Forecasts (Value in USD)
- 5.1 By Payment Model
- 5.1.1 Bundled Payments
- 5.1.2 Shared Savings (ACO)
- 5.1.3 Pay-for-Performance
- 5.1.4 Patient-Centred Medical Home (PCMH)
- 5.1.5 Capitation/Global Budgets
- 5.1.6 Episode-based Payments
- 5.1.7 Other Emerging Models
- 5.2 By Provider Setting
- 5.2.1 Hospitals & IDNs
- 5.2.2 Physician Group Practices
- 5.2.3 Home Health & Post-Acute Care
- 5.2.4 Ambulatory Surgical Centres
- 5.2.5 Virtual/Tele-health Providers
- 5.2.6 Other Provider Settings
- 5.3 By Geography
- 5.3.1 North America
- 5.3.1.1 United States
- 5.3.1.2 Canada
- 5.3.1.3 Mexico
- 5.3.2 Europe
- 5.3.2.1 Germany
- 5.3.2.2 United Kingdom
- 5.3.2.3 France
- 5.3.2.4 Italy
- 5.3.2.5 Spain
- 5.3.2.6 Rest of Europe
- 5.3.3 Asia-Pacific
- 5.3.3.1 China
- 5.3.3.2 Japan
- 5.3.3.3 India
- 5.3.3.4 Australia
- 5.3.3.5 South Korea
- 5.3.3.6 Rest of Asia-Pacific
- 5.3.4 Middle East & Africa
- 5.3.4.1 GCC
- 5.3.4.2 South Africa
- 5.3.4.3 Rest of Middle East & Africa
- 5.3.5 South America
- 5.3.5.1 Brazil
- 5.3.5.2 Argentina
- 5.3.5.3 Rest of South America
- 5.3.1 North America
6 Competitive Landscape
- 6.1 Market Concentration
- 6.2 Market Share Analysis
- 6.3 Company Profiles (includes Global level Overview, Market level overview, Core Segments, Financials as available, Strategic Information, Market Rank/Share for key companies, Products & Services, and Recent Developments)
- 6.3.1 UnitedHealth Group (Optum)
- 6.3.2 Humana Inc.
- 6.3.3 CVS Health (Aetna)
- 6.3.4 Elevance Health (Anthem)
- 6.3.5 Cigna Healthcare
- 6.3.6 Kaiser Permanente
- 6.3.7 Blue Cross Blue Shield
- 6.3.8 MVP Health Care
- 6.3.9 Agilon Health
- 6.3.10 Aledade
- 6.3.11 Signify Health
- 6.3.12 Evolent Health
- 6.3.13 Lumeris
- 6.3.14 Conifer Health Solutions
- 6.3.15 Privia Health
- 6.3.16 Oak Street Health
- 6.3.17 VillageMD
- 6.3.18 ChenMed
- 6.3.19 CareMore Health
- 6.3.20 Centene Corp.
- 6.3.21 Clover Health
- 6.3.22 Health Catalyst
- 6.3.23 GuideWell (Florida Blue)
7 Market Opportunities & Future Outlook
- 7.1 White-space & Unmet-Need Assessment

