PUBLISHER: Mordor Intelligence | PRODUCT CODE: 2154353

PUBLISHER: Mordor Intelligence | PRODUCT CODE: 2154353
Amyloidosis Therapeutics - Market Share Analysis, Industry Trends & Statistics, Growth Forecasts (2026 - 2031)
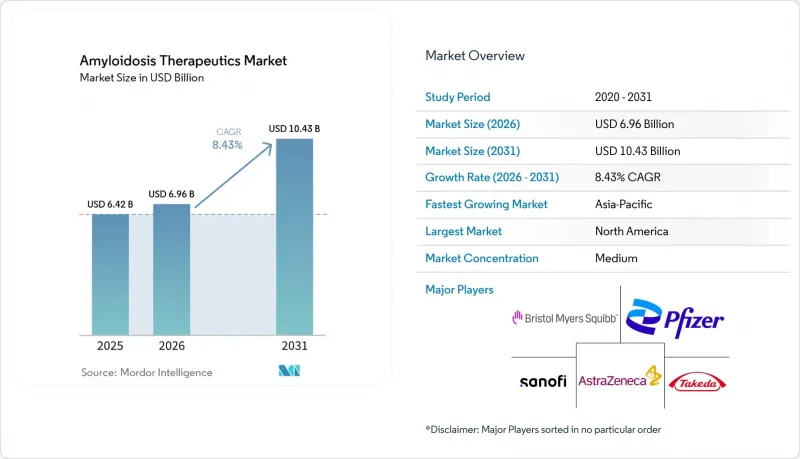
According to Mordor Intelligence, the amyloidosis therapeutics market was valued at USD 6.42 billion in 2025 and is estimated to reach USD 6.96 billion in 2026.
Global Amyloidosis Therapeutics Market Trends and Insights
Regulatory Approvals of Disease-Modifying Therapies
Regulatory activity between 2024 and 2026 has changed treatment choices in the amyloidosis therapeutics market. The FDA approved acoramidis for ATTR-CM in November 2024 after the ATTRibute-CM study reported a 42% reduction in the composite of all-cause mortality and recurrent cardiovascular hospitalizations over 30 months among 632 participants. The FDA then approved vutrisiran for ATTR-CM in March 2025, extending an RNA interference option across cardiomyopathy and polyneuropathy manifestations htm. Its approvals in the United States, Brazil, the European Union, and Canada may shorten the period before local coverage decisions because payers can compare decisions across markets. The traditional FDA approval of daratumumab-hyaluronidase-fihj plus VCd for newly diagnosed AL amyloidosis in November 2025 reinforced an established regimen after extended ANDROMEDA follow-up. These decisions increase the need for manufacturers to show practical value in addition to clinical benefit.
Aging Population and ATTR-CM Identification
ATTR cardiomyopathy mainly affects adults older than 65 years, and the incidence in the United States increased through 2023. Claims-based evidence reported ATTR-CM prevalence of 54.9 per million among older adults in the United States. Autopsy findings have also identified cardiac amyloid deposits in people who were not recognized clinically, indicating that diagnosed prevalence does not capture the full clinical burden. Earlier recognition can add new patients to the treated population without requiring patients to switch therapies. Japan has a reported ATTR-CM prevalence of 100 per million per year, which supports demand as its diagnosis pathway develops. Orphan-drug pathways administered by regulators such as the FDA and EMA also remain important for clinical development in rare diseases.
High Treatment and Lifetime Disease-Management Costs
The cost of long-term treatment can restrict access despite regulatory approval. AL amyloidosis care also requires resource-intensive anti-plasma-cell regimens, which can raise total healthcare use. Frequency-adjusted daratumumab regimens have been studied partly to reduce treatment intensity while maintaining efficacy. Patients with coverage can still face repeated prior authorization and the risk of delayed continuation. In Brazil, South Africa, and Gulf Cooperation Council states, the lack of rare-disease funding structures may delay reimbursed access after authorization. These limits can slow revenue realization in the amyloidosis therapeutics market even when the medical need is clear.
Other drivers and restraints analyzed in the detailed report include:
- AI-Enabled Echocardiography and PYP Referral Pathways
- Rising Disease Awareness and Earlier Diagnosis
- Payer Prior Authorization and Site-of-Care Fragmentation
For complete list of drivers and restraints, kindly check the Table Of Contents.
Segment Analysis
AL amyloidosis accounted for 42.57% of the amyloidosis therapeutics market share in 2025. Its revenue position reflects long-standing clinical infrastructure for plasma-cell-directed treatment and high therapy cost per patient. The November 2025 traditional approval of daratumumab-hyaluronidase-fihj plus VCd established a durable standard for newly diagnosed AL amyloidosis. The extended ANDROMEDA follow-up reported a hazard ratio of 0.62 for overall survival. This treatment pathway supports continued demand for multi-agent anti-plasma-cell regimens.
ATTR amyloidosis is projected to record the fastest growth at 8.89% CAGR through 2031. More approved therapies and improved detection of older adults with unexplained heart failure support this expansion. AA amyloidosis remains the smallest revenue category and is primarily addressed by controlling its underlying inflammatory disease. IL-6 targeted biologics may indirectly affect care in this group. ATTR is likely to add patients faster, while AL retains higher revenue per patient because its treatment can include layered drug regimens. Regulatory requirements for orphan therapies continue to influence trial design and post-marketing monitoring across types.
TTR stabilizers held 38.93% of the amyloidosis therapeutics market share in 2025. Oral tafamidis and acoramidis support this position in the ATTR-CM population. Stabilizers remain familiar to prescribers and fit routine outpatient use. Gene silencers are forecast to expand at 9.23% CAGR through 2031. Vutrisiran’s ATTR-CM approval and eplontersen’s established use in hereditary ATTR polyneuropathy have broadened the clinical role of this therapy class.
Amyloid depleters have yet to establish an approved role in AL amyloidosis. Prothena discontinued birtamimab in May 2025 after the Phase 3 AFFIRM-AL trial did not meet its primary endpoint in Mayo Stage IV AL amyloidosis. Attention has consequently shifted toward ATTR-focused antibodies, including ALXN2220 and coramitug. Anti-plasma-cell and chemotherapy regimens remain important in AL treatment. Formulary decisions made around stabilizer-first care are likely to be reassessed as cardiovascular outcome evidence for silencers accumulates. The amyloidosis therapeutics industry is thus balancing established oral treatment with newer approaches that reduce TTR production.
Complete Report Scope:
- By Amyloidosis Type
- ATTR Amyloidosis
- AL Amyloidosis
- AA Amyloidosis
- Others
- By Therapy Class
- TTR Stabilizers
- Gene Silencers
- Amyloid Depleters
- Anti-Plasma-Cell and Chemotherapy Regimens
- Organ Transplantation
- Others
- By Drug Modality
- Small-Molecule Therapies
- RNA Interference Therapies
- Plasma-Derived and Recombinant Therapies
- Monoclonal Antibodies
- Others
- By Formulation
- Tablets
- Capsules
- Prefilled Syringes
- Vials and Infusion Products
- By Route of Administration
- Oral
- Intravenous
- Subcutaneous
- Others
- By End User
- Hospitals
- Specialty Clinics
- Ambulatory Surgical Centers (ASCs)
- Others
- By Geography
- North America
- United States
- Canada
- Mexico
- Europe
- Germany
- United Kingdom
- France
- Italy
- Spain
- Rest of Europe
- Asia-Pacific
- China
- India
- Japan
- Australia
- South Korea
- Rest of Asia-Pacific
- Middle East and Africa
- GCC
- South Africa
- Rest of Middle East and Africa
- South America
- Brazil
- Argentina
- Rest of South America
- North America
Geography Analysis
North America held 39.55% of the amyloidosis therapeutics market share in 2025. The United States combines active FDA decisions, established specialty pharmacy networks, and broad commercial coverage for vutrisiran. Among Medicare-eligible people, ATTR-CM incidence was 44.3 per 100,000 person-years in 2021 and had increased over time. This suggests that the identified disease remains below the potential prevalence level. Health Canada approved vutrisiran for ATTR-CM in December 2025, supporting Canadian uptake in 2026.
Europe added several important approvals during 2025. The European Commission authorized vutrisiran for ATTR-CM in June 2025. Germany's benefit evaluations for acoramidis and vutrisiran provide reference points for reimbursement negotiations. NHS England's Midlands Amyloidosis Service extended access beyond London's National Amyloidosis Center.
Asia-Pacific is expected to record a 12.29% CAGR through 2031, the fastest rate among regions. Japan's ATTR-CM prevalence of 100 per million per year offers a large patient base as identification improves. Acoramidis received Japanese approval in March 2025, giving Japan access to both major TTR stabilizer classes. China has established a precedent for ATTR treatment through tafamidis, while AstraZeneca is studying eplontersen in Chinese ATTR-CM patients. Brazil approved vutrisiran for ATTR-CM in March 2025, but access elsewhere remains limited by specialist capacity and patient costs.
- Alexion Pharmaceuticals, Inc.
- Alnylam Pharmaceuticals
- Amgen
- Arcturus Therapeutics Holdings Inc.
- AstraZeneca
- Attralus, Inc.
- BridgeBio Pharma, Inc.
- Bristol-Myers Squibb
- Corino Therapeutics, Inc.
- CRISPR Therapeutics AG
- CSL Behring
- Roche
- GlaxoSmithKline
- Intellia Therapeutics, Inc.
- Ionis Pharmaceuticals
- Johnson & Johnson
- Neurimmune AG
- Novartis
- Oncopeptides AB
- Pfizer
- Prothena Corporation plc
- Regeneron Pharmaceuticals
- Sanofi
- SOM Biotech, S.L.
- Takeda Pharmaceuticals
Additional Benefits:
- The market estimate (ME) sheet in Excel format
- 3 months of analyst support
TABLE OF CONTENTS
1 Introduction
- 1.1 Study Assumptions & Market Definition
- 1.2 Scope of the Study
2 Research Methodology
3 Executive Summary
4 Market Landscape
- 4.1 Market Overview
- 4.2 Market Drivers
- 4.2.1 Rising Disease Awareness and Earlier Diagnosis
- 4.2.2 Aging Population and ATTR-CM Identification
- 4.2.3 Regulatory Approvals of Disease-Modifying Therapies
- 4.2.4 Expansion of Specialized Amyloidosis Care Centers
- 4.2.5 AI-Enabled Echocardiography and PYP Referral Pathways
- 4.2.6 Genotype-Guided Therapy and Companion Diagnostics
- 4.3 Market Restraints
- 4.3.1 High Treatment and Lifetime Disease-Management Costs
- 4.3.2 Limited Patient Pools for Clinical-Trial Recruitment
- 4.3.3 Payer Prior Authorization and Site-of-Care Fragmentation
- 4.3.4 Limited RNAi Manufacturing and Cold-Chain Capacity
- 4.4 Value/Supply-Chain Analysis
- 4.5 Regulatory Landscape
- 4.6 Technological Outlook
- 4.7 Porter's Five Forces
- 4.7.1 Threat of New Entrants
- 4.7.2 Bargaining Power of Buyers
- 4.7.3 Bargaining Power of Suppliers
- 4.7.4 Threat of Substitutes
- 4.7.5 Intensity of Rivalry
5 Market Size & Growth Forecasts (Value, USD)
- 5.1 By Amyloidosis Type
- 5.1.1 ATTR Amyloidosis
- 5.1.2 AL Amyloidosis
- 5.1.3 AA Amyloidosis
- 5.1.4 Others
- 5.2 By Therapy Class
- 5.2.1 TTR Stabilizers
- 5.2.2 Gene Silencers
- 5.2.3 Amyloid Depleters
- 5.2.4 Anti-Plasma-Cell and Chemotherapy Regimens
- 5.2.5 Organ Transplantation
- 5.2.6 Others
- 5.3 By Drug Modality
- 5.3.1 Small-Molecule Therapies
- 5.3.2 RNA Interference Therapies
- 5.3.3 Plasma-Derived and Recombinant Therapies
- 5.3.4 Monoclonal Antibodies
- 5.3.5 Others
- 5.4 By Formulation
- 5.4.1 Tablets
- 5.4.2 Capsules
- 5.4.3 Prefilled Syringes
- 5.4.4 Vials and Infusion Products
- 5.5 By Route of Administration
- 5.5.1 Oral
- 5.5.2 Intravenous
- 5.5.3 Subcutaneous
- 5.5.4 Others
- 5.6 By End User
- 5.6.1 Hospitals
- 5.6.2 Specialty Clinics
- 5.6.3 Ambulatory Surgical Centers (ASCs)
- 5.6.4 Others
- 5.7 By Geography
- 5.7.1 North America
- 5.7.1.1 United States
- 5.7.1.2 Canada
- 5.7.1.3 Mexico
- 5.7.2 Europe
- 5.7.2.1 Germany
- 5.7.2.2 United Kingdom
- 5.7.2.3 France
- 5.7.2.4 Italy
- 5.7.2.5 Spain
- 5.7.2.6 Rest of Europe
- 5.7.3 Asia-Pacific
- 5.7.3.1 China
- 5.7.3.2 India
- 5.7.3.3 Japan
- 5.7.3.4 Australia
- 5.7.3.5 South Korea
- 5.7.3.6 Rest of Asia-Pacific
- 5.7.4 Middle East and Africa
- 5.7.4.1 GCC
- 5.7.4.2 South Africa
- 5.7.4.3 Rest of Middle East and Africa
- 5.7.5 South America
- 5.7.5.1 Brazil
- 5.7.5.2 Argentina
- 5.7.5.3 Rest of South America
- 5.7.1 North America
6 Competitive Landscape
- 6.1 Market Concentration
- 6.2 Market Share Analysis
- 6.3 Company Profiles (includes Global Level Overview, Market Level Overview, Core Segments, Financials as Available, Strategic Information, Market Rank/Share for Key Companies, Products & Services, and Recent Developments)
- 6.3.1 Alexion Pharmaceuticals, Inc.
- 6.3.2 Alnylam Pharmaceuticals, Inc.
- 6.3.3 Amgen Inc.
- 6.3.4 Arcturus Therapeutics Holdings Inc.
- 6.3.5 AstraZeneca PLC
- 6.3.6 Attralus, Inc.
- 6.3.7 BridgeBio Pharma, Inc.
- 6.3.8 Bristol Myers Squibb Company
- 6.3.9 Corino Therapeutics, Inc.
- 6.3.10 CRISPR Therapeutics AG
- 6.3.11 CSL Limited
- 6.3.12 F. Hoffmann-La Roche Ltd
- 6.3.13 GSK plc
- 6.3.14 Intellia Therapeutics, Inc.
- 6.3.15 Ionis Pharmaceuticals, Inc.
- 6.3.16 Johnson & Johnson Services, Inc.
- 6.3.17 Neurimmune AG
- 6.3.18 Novartis AG
- 6.3.19 Oncopeptides AB
- 6.3.20 Pfizer Inc.
- 6.3.21 Prothena Corporation plc
- 6.3.22 Regeneron Pharmaceuticals, Inc.
- 6.3.23 Sanofi
- 6.3.24 SOM Biotech, S.L.
- 6.3.25 Takeda Pharmaceutical Company Limited
7 Market Opportunities & Future Outlook
- 7.1 White-Space & Unmet-Need Assessment

