PUBLISHER: Mordor Intelligence | PRODUCT CODE: 2120722

PUBLISHER: Mordor Intelligence | PRODUCT CODE: 2120722
Clinical Trials - Market Share Analysis, Industry Trends & Statistics, Growth Forecasts (2026 - 2031)
According to Mordor Intelligence, the clinical trials market size was valued at USD 90.44 billion in 2025 and is estimated to grow from USD 95.97 billion in 2026 to reach USD 131.55 billion by 2031, at a CAGR of 6.51% during the forecast period (2026-2031).
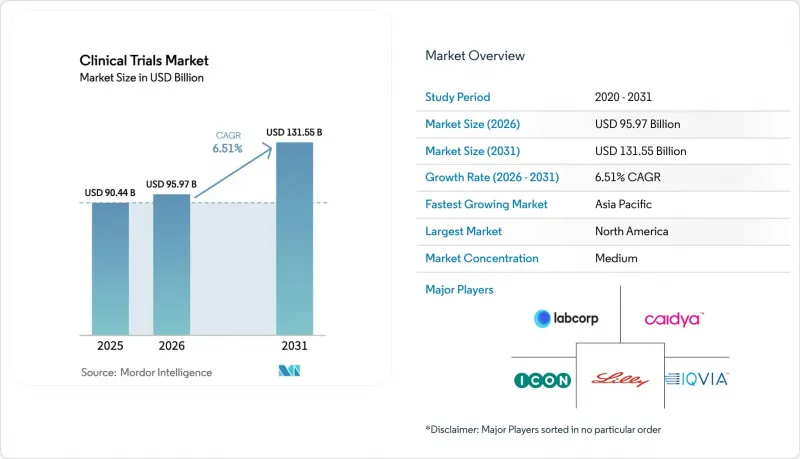
This report is Segmented by Phase (Phase I, and More), Study Design (Interventional/Treatment Studies, and More), Service Type (Protocol Design & Feasibility, and More), Therapeutic Area (Oncology, and More), Sponsor Type (Pharmaceutical & Biopharmaceutical Companies, and More), and Geography (North America, Europe, Asia, and More). The Market Forecasts are Provided in Terms of Value (USD).
Global Clinical Trials Market Trends and Insights
Growing Volume of Complex Biologics and Precision Medicines Requiring Extensive Trials
Biologics and precision medicines represented 38% of all investigational assets in 2025, up from 29% five years earlier, driving increased demand for longer and data-intensive studies[1]. Cell-and-gene therapy programs needed 1,847 active INDs in the United States during 2025, yet viral-vector capacity constraints meant just 64% of planned protocols actually initiated on schedule. CROs have started acquiring manufacturing assets to mitigate these delays; Thermo Fisher invested USD 420 million to double vector capacity by 2027. Monoclonal-antibody Phase III studies averaged 52 months in 2025, compared to 38 months for small molecules, thereby elevating demand for platforms that manage four to six terabytes of genomic and imaging data per trial.
Expanded Outsourcing to Full-Service CROs for Cost and Speed Advantages
Pharmaceutical sponsors outsourced 73% of their clinical budgets to CROs in 2025 and secured Phase III enrollment 5.3 months faster than in-house programs. IQVIA posted USD 29.4 billion in backlog, equal to 2.1 years of revenue visibility, while Medpace hit a 94% on-time database-lock rate by embedding oncology nurses at sites. Asian CROs still offer a three-to-one cost edge, although 14 Indian sites received FDA warning letters in 2025 for GCP lapses, signaling that quality oversight remains critical.
High Attrition Rates in Oncology and CNS Trials Increasing Cost Risk
Oncology protocols posted a 52% Phase III failure rate in 2025, driven by tumor heterogeneity and stringent payer demands for overall survival data. Alzheimer's programs fared worse, with a 68% failure rate, causing each unsuccessful study to absorb USD 180-240 million in sunk costs. Adaptive designs help mitigate risk; Roche's 2025 basket trial trimmed enrollment by 34% and saved USD 62 million by dropping weak cohorts mid-stream. Germany's IQWiG rejected 41% of oncology submissions in 2025, prompting sponsors to focus on more rigorous endpoints[2].
Other drivers and restraints analyzed in the detailed report include:
- Regulatory Reforms Accelerating Approval Pathways
- Pandemic-Induced Digital Transformation Driving eClinical Adoption
- Stringent Data-Privacy Legislations Limiting Cross-Border Data Flows
For complete list of drivers and restraints, kindly check the Table Of Contents.
Segment Analysis
Phase II studies are projected to grow at a 6.80% CAGR through 2031 and captured rising interest as adaptive methodologies optimize dose-finding and efficacy confirmation inside a single protocol. Novartis used Bayesian randomization in 2025 to shift enrollment toward high-performing arms, trimming total exposure by 28%. Despite Phase III's 55% clinical trials market share in 2025, its duration and attrition rates spur sponsors to invest earlier in seamless Phase II/III pathways that may condense timelines by 9-12 months. Phase I programs benefit from micro-dosing and rapid mass-spectrometry assays that deliver PK data within 48 hours, while Phase IV studies piggyback on pivotal trials to amortize site costs.
Interventional trials accounted for 72.30% of 2025 revenue, yet pragmatic and observational approaches are also essential for generating real-world evidence. EMA guidance allows label expansions supported by observational datasets of at least 1,200 subjects adjusted by propensity scores[3]. Expanded-access programs accounted for 4% of total activity and helped build physician familiarity ahead of launches. The NIH funded 11 pragmatic megatrials in 2025 that utilized electronic health-record randomization to reduce costs by two-thirds.
Complete Report Scope:
- By Phase
- Phase I
- Phase II
- Phase III
- Phase IV
- By Study Design
- Interventional / Treatment Studies
- Observational Studies
- Expanded Access Studies
- By Service Type
- Protocol Design & Feasibility
- Site Identification & Start-Up
- Regulatory Submission & Approval
- Clinical Trial Monitoring
- Data Management & Biostatistics
- Medical Writing
- Other Service Types
- By Therapeutic Area
- Oncology
- Cardiovascular
- Neurology
- Infectious Diseases
- Metabolic Disorders (Diabetes, Obesity)
- Immunology / Autoimmune
- Other Therapeutic Areas
- By Sponsor Type
- Pharmaceutical & Biopharmaceutical Companies
- Medical Device Companies
- Academic & Research Institutes
- Government & Non-Profit Organizations
- Geography
- North America
- United States
- Canada
- Mexico
- Europe
- Germany
- United Kingdom
- France
- Italy
- Spain
- Rest Of Europe
- Asia-Pacific
- China
- Japan
- India
- South Korea
- Australia
- Rest Of Asia-Pacific
- Middle-East And Africa
- GCC
- South Africa
- Rest Of Middle East And Africa
- South America
- Brazil
- Argentina
- Rest Of South America
- North America
Geography Analysis
North America controlled 49.20% of global revenue in 2025, stoked by FDA incentives, a high site density, and enrollment rates of 1.2 patients per site each month, 40% above Europe. Canada added 6% of regional studies, benefiting from protocol alignment with the United States, while Mexico gained prominence as ICON's 2025 operations hub targeted 30% cost savings.
Asia-Pacific outpaced all regions at 7.90% CAGR through 2031, powered by China's 62 IND clearances in 2025 and India's 30-40% per-patient cost advantages. Conditional approvals for regenerative medicines in Japan and a 43.5% R&D tax refund in Australia further widened the region's appeal. South Korea leveraged its national insurance database to supply real-world comparators for single-arm oncology designs.
Europe captured 28% market share in 2025 after the Clinical Trials Regulation slashed average approval time to 10 months and enabled simultaneous multi-country site activation. The UK's rolling-review model enticed 14 rare-disease protocols in 2025. GCC nations funded landmark diabetes and oncology studies to diversify health economies, while Brazil and Argentina together made up 4% of global volume despite currency and import bottlenecks.
- ACM Global Laboratories
- Aragen Life Sciences Ltd.
- Caidya
- Charles River
- ClinChoice
- ICON
- IQVIA
- KCR S.A.
- Laboratory Corporation Of America Holdings (Labcorp)
- Lilly (Lilly Clinical Innovation)
- MedPace
- Novotech
- Parexel International Corp.
- Pfizer
- Pharmaron Inc.
- Syneos Health
- Thermo Fisher Scientific Inc. (PPD)
- Wuxi AppTec Co. Ltd.
Additional Benefits:
- The market estimate (ME) sheet in Excel format
- 3 months of analyst support
TABLE OF CONTENTS
1 Introduction
- 1.1 Study Assumptions & Market Definition
- 1.2 Scope of the Study
2 Research Methodology
3 Executive Summary
4 Market Landscape
- 4.1 Market Overview
- 4.2 Market Drivers
- 4.2.1 Growing Volume of Complex Biologics & Precision Medicines Requiring Extensive Trials
- 4.2.2 Expanded Outsourcing to Full-Service CROs for Cost & Speed Advantages
- 4.2.3 Regulatory Reforms Accelerating Approval Pathways (E.G., FDA Fast Track, EMA PRIME)
- 4.2.4 Pandemic-Induced Digital Transformation Driving Eclinical Adoption
- 4.2.5 Rise of Patient-Owned Health Data Wallets Facilitating Remote Monitoring
- 4.2.6 Blockchain-Based Consent Management Enhancing Auditability & Compliance
- 4.3 Market Restraints
- 4.3.1 High Attrition Rates in Oncology and CNS Trials Increasing Cost Risk
- 4.3.2 Stringent Data-Privacy Legislations Limiting Cross-Border Data Flows
- 4.3.3 Scarcity of GMP-Compliant Viral Vector Manufacturing Capacity for Gene Therapy Trials
- 4.3.4 Rising Carbon-Footprint Accountability Pressures on Multisite Trials
- 4.4 Regulatory Outlook
- 4.5 Porter's Five Forces Analysis
- 4.5.1 Threat Of New Entrants
- 4.5.2 Bargaining Power Of Buyers
- 4.5.3 Bargaining Power Of Suppliers
- 4.5.4 Threat Of Substitutes
- 4.5.5 Intensity Of Competitive Rivalry
5 Market Size & Growth Forecasts (Value, USD)
- 5.1 By Phase
- 5.1.1 Phase I
- 5.1.2 Phase II
- 5.1.3 Phase III
- 5.1.4 Phase IV
- 5.2 By Study Design
- 5.2.1 Interventional / Treatment Studies
- 5.2.2 Observational Studies
- 5.2.3 Expanded Access Studies
- 5.3 By Service Type
- 5.3.1 Protocol Design & Feasibility
- 5.3.2 Site Identification & Start-Up
- 5.3.3 Regulatory Submission & Approval
- 5.3.4 Clinical Trial Monitoring
- 5.3.5 Data Management & Biostatistics
- 5.3.6 Medical Writing
- 5.3.7 Other Service Types
- 5.4 By Therapeutic Area
- 5.4.1 Oncology
- 5.4.2 Cardiovascular
- 5.4.3 Neurology
- 5.4.4 Infectious Diseases
- 5.4.5 Metabolic Disorders (Diabetes, Obesity)
- 5.4.6 Immunology / Autoimmune
- 5.4.7 Other Therapeutic Areas
- 5.5 By Sponsor Type
- 5.5.1 Pharmaceutical & Biopharmaceutical Companies
- 5.5.2 Medical Device Companies
- 5.5.3 Academic & Research Institutes
- 5.5.4 Government & Non-Profit Organizations
- 5.6 Geography
- 5.6.1 North America
- 5.6.1.1 United States
- 5.6.1.2 Canada
- 5.6.1.3 Mexico
- 5.6.2 Europe
- 5.6.2.1 Germany
- 5.6.2.2 United Kingdom
- 5.6.2.3 France
- 5.6.2.4 Italy
- 5.6.2.5 Spain
- 5.6.2.6 Rest Of Europe
- 5.6.3 Asia-Pacific
- 5.6.3.1 China
- 5.6.3.2 Japan
- 5.6.3.3 India
- 5.6.3.4 South Korea
- 5.6.3.5 Australia
- 5.6.3.6 Rest Of Asia-Pacific
- 5.6.4 Middle-East And Africa
- 5.6.4.1 GCC
- 5.6.4.2 South Africa
- 5.6.4.3 Rest Of Middle East And Africa
- 5.6.5 South America
- 5.6.5.1 Brazil
- 5.6.5.2 Argentina
- 5.6.5.3 Rest Of South America
- 5.6.1 North America
6 Competitive Landscape
- 6.1 Market Concentration
- 6.2 Market Share Analysis
- 6.3 Company Profiles (Includes Global Level Overview, Market Level Overview, Core Business Segments, Financials, Headcount, Key Information, Market Rank, Market Share, Products And Services, And Analysis Of Recent Developments)
- 6.3.1 ACM Global Laboratories
- 6.3.2 Aragen Life Sciences Ltd.
- 6.3.3 Caidya
- 6.3.4 Charles River Laboratories International Inc.
- 6.3.5 ClinChoice
- 6.3.6 ICON Plc
- 6.3.7 IQVIA Holdings Inc.
- 6.3.8 KCR S.A.
- 6.3.9 Laboratory Corporation Of America Holdings (Labcorp)
- 6.3.10 Lilly (Lilly Clinical Innovation)
- 6.3.11 Medpace Holdings Inc.
- 6.3.12 Novotech
- 6.3.13 Parexel International Corp.
- 6.3.14 Pfizer Inc.
- 6.3.15 Pharmaron Inc.
- 6.3.16 Syneos Health
- 6.3.17 Thermo Fisher Scientific Inc. (PPD)
- 6.3.18 Wuxi AppTec Co. Ltd.
7 Market Opportunities & Future Outlook
- 7.1 White-Space & Unmet-Need Assessment

