PUBLISHER: Mordor Intelligence | PRODUCT CODE: 2155327

PUBLISHER: Mordor Intelligence | PRODUCT CODE: 2155327
Interchangeable Biosimilars - Market Share Analysis, Industry Trends & Statistics, Growth Forecasts (2026 - 2031)
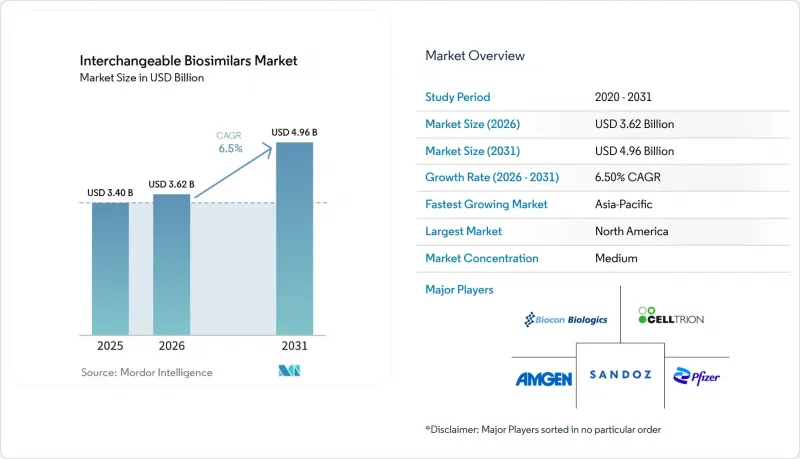
According to Mordor Intelligence, the interchangeable biosimilars market size was valued at USD 3.40 billion in 2025 and is estimated to grow from USD 3.62 billion in 2026 to reach USD 4.96 billion by 2031, at a CAGR of 6.5% during the forecast period (2026-2031).
Global Interchangeable Biosimilars Market Trends and Insights
Patent Expiry of High-Value Biologics
A study published in 2026 identified a USD 234 billion opportunity associated with 118 biologics expected to lose U.S. exclusivity through 2034. As of mid-2024, only 12 biosimilars for these molecules were in development, indicating less crowded opportunities for developers that can fund complex programs. The 2026-2029 period includes major oncology patent expiries, increasing development interest in large biologic therapies. Formycon reported positive clinical data for FYB206, its pembrolizumab biosimilar candidate, in 2025. Alvotech's 2026 vedolizumab filings indicate that developers are pursuing interchangeability from the outset, increasing competition for formulary access as reference biologics lose protection.
Pharmacy-Level Substitution Potential
Pharmacy-level substitution provides the interchangeable biosimilars market with a practical advantage in dispensing settings where state laws permit substitution. A 2025 JAMA Health Forum study found that insulin glargine biosimilar dispensing increased by more than 47,000 prescriptions after Semglee received an interchangeable designation in November 2021. The increase occurred across retail, mail, and long-term care channels, demonstrating the designation's impact across dispensing pathways. California considered SB 1094 in 2026 to permit substitution of non-interchangeable biosimilars, while Tennessee enacted 2025 legislation allowing health carriers to require biosimilar use without an interchangeable designation. Commercial adoption continues to depend on payer policies and pharmacy operations.
State-Level Variation in Automatic Substitution Laws
State-level variation limits the operational simplicity that interchangeability is intended to provide. A 2025 analysis reported that 90% of states imposed stricter requirements for interchangeable biologics than for generic drugs, including prescriber notification, record retention, and, in some cases, written consent. These requirements increase pharmacy workloads, particularly when systems do not readily connect with prescriber networks. A JAMA Health Forum study reported lower substitution rates in states with more restrictive notification requirements. This finding indicates that an FDA designation alone does not ensure consistent dispensing practices across states. The FDA applies interchangeability between a biosimilar and its named reference product, rather than among biosimilars for the same molecule, which can complicate formulary changes when multiple options are available.
Other drivers and restraints analyzed in the detailed report include:
- Payer Pressure to Reduce Biologic Treatment Costs
- Expansion of Interchangeable Designations Across Major Molecules
- Reimbursement and Channel-Contracting Complexity
For complete list of drivers and restraints, kindly check the Table Of Contents.
Segment Analysis
Interchangeable monoclonal antibodies accounted for 47.45% of revenue in 2025, representing the largest interchangeable biosimilars market share by product type. Their position reflected the commercial importance of adalimumab and ustekinumab, where manufacturers competed for payer coverage and pharmacy access. Denosumab also emerged as a competitive product category, shifting focus toward supply reliability and payer contracting.
Interchangeable insulins are forecast to grow at a CAGR of 7.45% through 2031, the highest among product types. Established retail and mail-order prescription workflows make interchangeability more practical for insulin dispensing. Increased insulin glargine dispensing following Semglee's designation supported this trend. Growth factors, fusion proteins, and recombinant proteins remain smaller segments due to cold-chain and device requirements.
Autoimmune and inflammatory diseases accounted for 39.76% of revenue in 2025, retaining the largest therapeutic-area share. Rheumatoid arthritis, psoriatic arthritis, and inflammatory bowel disease have large treated populations and established biologic prescribing patterns. Adalimumab biosimilars achieved meaningful formulary placement across major payer networks, while step-therapy protocols supported recurring demand.
Oncology and hematology are projected to expand at a CAGR of 7.98% through 2031, making it the fastest-growing therapeutic area. Samsung Bioepis reported that bevacizumab, rituximab, and trastuzumab biosimilars reached average market shares of 52% to 81% five years after launch. Growth is driven by pipeline development, as these molecules have biosimilar competition but no interchangeable entry. Diabetes and ophthalmic care also contribute through insulin glargine, ranibizumab, and aflibercept alternatives.
Complete Report Scope:
- By Product Type
- Interchangeable Monoclonal Antibodies
- Interchangeable Insulins
- Interchangeable Growth Factors
- Interchangeable Fusion Proteins
- Interchangeable Recombinant Proteins
- Other Interchangeable Biological Products
- By Therapeutic Area
- Autoimmune and Inflammatory Diseases
- Oncology and Hematology
- Diabetes
- Ophthalmic Diseases
- Others
- By Distribution Channel
- Specialty Pharmacies
- Retail Pharmacies
- Hospital Pharmacies
- Online Pharmacies
- Others
- By End User
- Hospitals and Clinics
- Ambulatory Infusion Centers
- Specialty Treatment Centers
- Others
- By Geography
- North America
- United States
- Canada
- Mexico
- Europe
- Germany
- United Kingdom
- France
- Italy
- Spain
- Rest of Europe
- Asia-Pacific
- China
- India
- Japan
- Australia
- South Korea
- Rest of Asia-Pacific
- Middle East and Africa
- GCC
- South Africa
- Rest of Middle East and Africa
- South America
- Brazil
- Argentina
- Rest of South America
- North America
Geography Analysis
North America held 40.35% of revenue in 2025, representing the largest regional share of the interchangeable biosimilars market. The United States has a distinct FDA pathway and a payer and PBM structure that enables large-scale formulary changes. CVS Caremark transitioned to preferred interchangeable ustekinumab biosimilars in July 2026, while CVS Health reported USD 3.3 billion in gross client savings from biosimilar adoption between April 2024 and December 2025. Canada follows provincial formulary processes, while Mexico remains more dependent on reference products in public procurement.
Asia-Pacific is forecast to grow at a CAGR of 8.76% through 2031, the fastest rate among regions. In September 2025, Japan's PMDA removed mandatory clinical study requirements specific to Japanese subjects, aligning more closely with international practices. Japan had 47 approved biosimilar products as of March 2026, although physicians continued to direct substitution decisions. China has not established a formal interchangeability framework, while India revised its Similar Biologics guidelines in May 2025 to strengthen analytical tools and align with major regulatory practices.
Europe operates under a different framework, as member states determine many substitution and prescribing policies. Denmark, the Netherlands, and France have adopted more active biosimilar-first approaches than several southern and eastern European markets. The Middle East and Africa and South America remain smaller contributors to the interchangeable biosimilars market due to reimbursement gaps, cold-chain infrastructure limitations, and constrained regulatory capacity. Regional progress depends on practical implementation as well as approval standards.
- Accord Healthcare Limited
- Alvotech
- Amgen
- Biocon Biologics Limited
- Bio-Thera Solutions, Ltd.
- Boehringer Ingelheim
- Celltrion, Inc.
- Cipla
- Coherus Biosciences
- Dr. Reddy's Laboratories
- Formycon AG
- Fresenius
- Innovent Biologics, Inc.
- Intas Pharmaceutical
- Lupin
- mAbxience S.L.
- Organon
- Pfizer
- Polpharma Biologics S.A.
- Samsung Bioepis Co., Ltd.
- Sandoz Group AG
- Teva Pharmaceutical Industries
- Viatris
- Zydus Lifesciences Limited
Additional Benefits:
- The market estimate (ME) sheet in Excel format
- 3 months of analyst support
TABLE OF CONTENTS
1 INTRODUCTION
- 1.1 Study Assumptions and Market Definition
- 1.2 Scope of the Study
2 RESEARCH METHODOLOGY
3 EXECUTIVE SUMMARY
4 MARKET LANDSCAPE
- 4.1 Market Overview
- 4.2 Market Drivers
- 4.2.1 Patent Expiry of High-Value Biologics
- 4.2.2 Pharmacy-Level Substitution Potential
- 4.2.3 Payer Pressure to Reduce Biologic Treatment Costs
- 4.2.4 Expansion of Interchangeable Designations Across Major Molecules
- 4.2.5 Formulary Automation and Specialty-Pharmacy Dispensing Data
- 4.2.6 Interchangeability-Enabled Demand Capture in Underserved Treatment Channels
- 4.3 Market Restraints
- 4.3.1 State-Level Variation in Automatic Substitution Laws
- 4.3.2 Reimbursement and Channel-Contracting Complexity
- 4.3.3 Interchangeability Confusion Among Prescribers and Patients
- 4.3.4 Limited Manufacturing Flexibility for Molecules Requiring Complex Cold-Chain and Device Operations
- 4.4 Value/Supply-Chain Analysis
- 4.5 Regulatory Landscape
- 4.6 Technological Outlook
- 4.7 Porter's Five Forces Analysis
- 4.7.1 Bargaining Power of Suppliers
- 4.7.2 Bargaining Power of Buyers
- 4.7.3 Threat of New Entrants
- 4.7.4 Threat of Substitutes
- 4.7.5 Competitive Rivalry
5 MARKET SIZE AND GROWTH FORECASTS (VALUE, USD)
- 5.1 By Product Type
- 5.1.1 Interchangeable Monoclonal Antibodies
- 5.1.2 Interchangeable Insulins
- 5.1.3 Interchangeable Growth Factors
- 5.1.4 Interchangeable Fusion Proteins
- 5.1.5 Interchangeable Recombinant Proteins
- 5.1.6 Other Interchangeable Biological Products
- 5.2 By Therapeutic Area
- 5.2.1 Autoimmune and Inflammatory Diseases
- 5.2.2 Oncology and Hematology
- 5.2.3 Diabetes
- 5.2.4 Ophthalmic Diseases
- 5.2.5 Others
- 5.3 By Distribution Channel
- 5.3.1 Specialty Pharmacies
- 5.3.2 Retail Pharmacies
- 5.3.3 Hospital Pharmacies
- 5.3.4 Online Pharmacies
- 5.3.5 Others
- 5.4 By End User
- 5.4.1 Hospitals and Clinics
- 5.4.2 Ambulatory Infusion Centers
- 5.4.3 Specialty Treatment Centers
- 5.4.4 Others
- 5.5 By Geography
- 5.5.1 North America
- 5.5.1.1 United States
- 5.5.1.2 Canada
- 5.5.1.3 Mexico
- 5.5.2 Europe
- 5.5.2.1 Germany
- 5.5.2.2 United Kingdom
- 5.5.2.3 France
- 5.5.2.4 Italy
- 5.5.2.5 Spain
- 5.5.2.6 Rest of Europe
- 5.5.3 Asia-Pacific
- 5.5.3.1 China
- 5.5.3.2 India
- 5.5.3.3 Japan
- 5.5.3.4 Australia
- 5.5.3.5 South Korea
- 5.5.3.6 Rest of Asia-Pacific
- 5.5.4 Middle East and Africa
- 5.5.4.1 GCC
- 5.5.4.2 South Africa
- 5.5.4.3 Rest of Middle East and Africa
- 5.5.5 South America
- 5.5.5.1 Brazil
- 5.5.5.2 Argentina
- 5.5.5.3 Rest of South America
- 5.5.1 North America
6 COMPETITIVE LANDSCAPE
- 6.1 Market Concentration
- 6.2 Market Share Analysis
- 6.3 Company Profiles (includes Global Level Overview, Market Level Overview, Core Segments, Financials as available, Strategic Information, Market Rank/Share, Products and Services, Recent Developments)
- 6.3.1 Accord Healthcare Limited
- 6.3.2 Alvotech
- 6.3.3 Amgen Inc.
- 6.3.4 Biocon Biologics Limited
- 6.3.5 Bio-Thera Solutions, Ltd.
- 6.3.6 Boehringer Ingelheim International GmbH
- 6.3.7 Celltrion, Inc.
- 6.3.8 Cipla Limited
- 6.3.9 Coherus BioSciences, Inc.
- 6.3.10 Dr. Reddy's Laboratories Limited
- 6.3.11 Formycon AG
- 6.3.12 Fresenius Kabi AG
- 6.3.13 Innovent Biologics, Inc.
- 6.3.14 Intas Pharmaceuticals Ltd.
- 6.3.15 Lupin Limited
- 6.3.16 mAbxience S.L.
- 6.3.17 Organon & Co.
- 6.3.18 Pfizer Inc.
- 6.3.19 Polpharma Biologics S.A.
- 6.3.20 Samsung Bioepis Co., Ltd.
- 6.3.21 Sandoz Group AG
- 6.3.22 Teva Pharmaceutical Industries Ltd.
- 6.3.23 Viatris Inc.
- 6.3.24 Zydus Lifesciences Limited
7 MARKET OPPORTUNITIES AND FUTURE OUTLOOK
- 7.1 White-Space and Unmet-Need Assessment

